
 Русский
 English
 Deutsch
 Español
 العربية
 中文
 Türkçe
 Français
 Italiano


What is a Herniated Disc?
An intervertebral disc is a cartilaginous "cushion" between vertebrae, consisting of two components: the annulus fibrosus (dense outer layer made of collagen fibers) and the nucleus pulposus (gel-like core, 80% water). The disc acts as a shock absorber during walking, running, and lifting, and enables spinal mobility.
A herniated disc occurs when the annulus fibrosus is damaged (tear or crack), and the nucleus pulposus protrudes beyond the disc boundary. The protruding fragment can compress the spinal cord, nerve roots, and blood vessels, causing pain, numbness, and limited mobility.
According to KBV (Kassenärztliche Bundesvereinigung), musculoskeletal diseases are the #1 reason for doctor visits in Germany — affecting more than 36.7 million patients annually. Herniated disc is one of the most common conditions leading to chronic back pain and disability.
Stages of disc herniation:
- Disc degeneration — initial stage: disc loses water and elasticity, annulus fibrosus thins, microtears appear. Pain may be absent
- Disc protrusion (prolapse) — disc bulging 2-5 mm without annulus fibrosus rupture. May compress nerve roots
- Extrusion — annulus fibrosus rupture, part of nucleus pulposus extends outward while remaining connected to the disc
- Sequestration — nucleus pulposus fragment completely separates and migrates into the spinal canal. Most dangerous stage
Most common locations:
- L4-L5 — between 4th and 5th lumbar vertebrae (most common location — up to 45% of all hernias)
- L5-S1 — lumbosacral junction (up to 35% of cases)
- L3-L4 — upper lumbar level (up to 5%)
- C5-C6, C6-C7 — cervical spine (up to 10%)
- Thoracic region — thoracic spine (less than 5%, but often with severe symptoms)
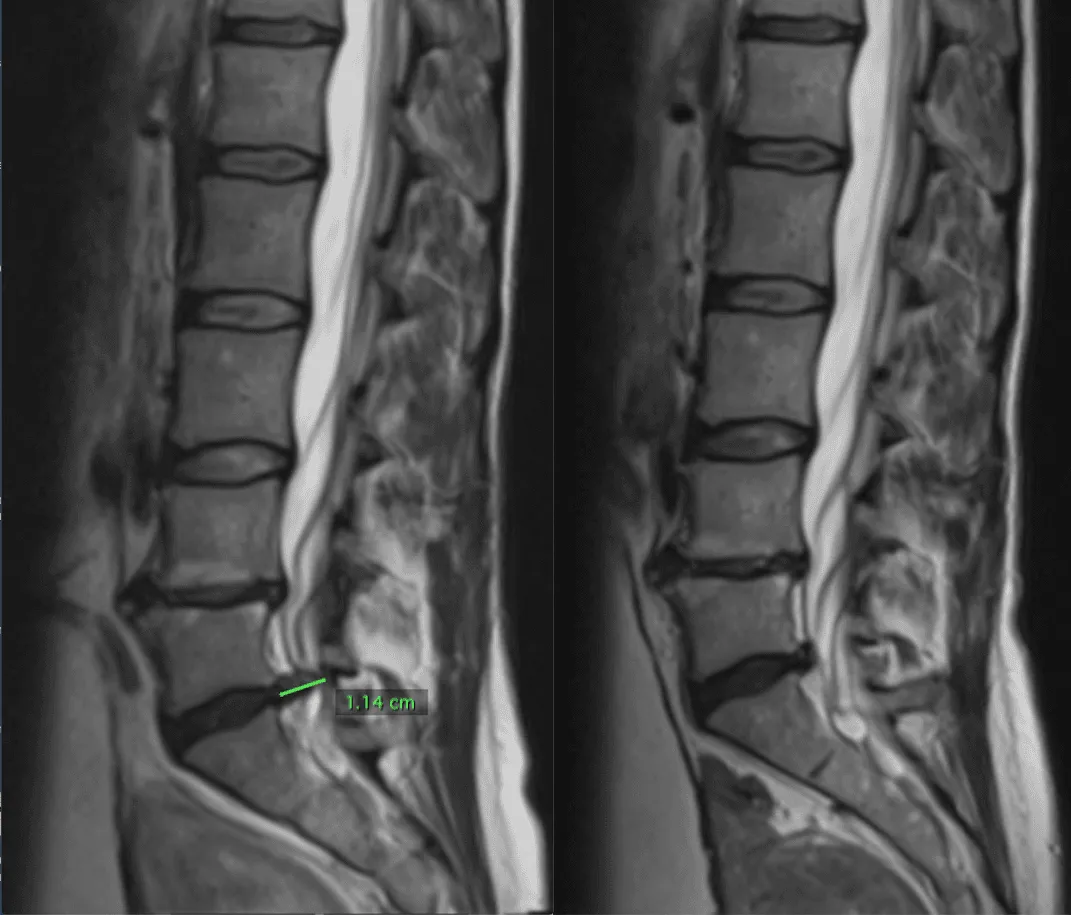
Facts about Herniated Disc
- ICD-10: M51.1 (lumbar), M50.1 (cervical)
- Frequency: 5-20 cases per 1000 people per year
- Peak age: 30-50 years
- Location: 90% — lumbar spine
- Recurrence after surgery: up to 15-25%
Causes and Risk Factors
Herniated disc is the result of a degenerative process that develops over years. The intervertebral disc receives nutrition not through blood vessels, but through diffusion — the seepage of nutrients from surrounding tissues during spine movement. This is why a sedentary lifestyle is one of the main factors of degeneration.
Main causes:
Degenerative changes
- Natural aging: with age, the disc loses up to 30% of its water content
- Osteochondrosis — degeneration of cartilage tissue
- Impaired metabolism in disc tissues
- Reduced elasticity of the annulus fibrosus
Mechanical factors
- Excessive physical stress on the spine
- Lifting heavy weights with improper technique
- Spinal injuries (car accidents, falls, sports)
- Prolonged forced posture (computer work)
Risk factors
- Excess weight (increased load on discs)
- Smoking (impairs blood supply to disc tissues)
- Genetic predisposition
- Occupational hazards (vibration, heavy labor)
- Sedentary lifestyle
Important to understand: herniated disc is not a "random event," but the result of a prolonged degenerative process. Traditional medicine offers surgical removal of the hernia, but this does not eliminate the cause — degeneration of the disc itself. This is why recurrences occur in 15-25% of cases after surgery. Whether regenerative treatment is an option in this condition is assessed by the clinic doctor.
Symptoms of Herniated Disc
Symptoms depend on the location and size of the hernia, as well as the degree of compression of neural structures. A hernia as small as 3-4 mm can cause significant pain if unfavorably positioned relative to the nerve root.
Lumbar spine (L4-L5, L5-S1)
- Acute or chronic low back pain (lumbalgia)
- Pain radiating to the buttock and leg along the sciatic nerve (sciatica)
- Numbness, tingling, "pins and needles" in the foot and toes
- Leg muscle weakness, foot drop
- Pain worsening with coughing, sneezing, straining
- Inability to stand or sit for long periods
- Antalgic posture — forced body position to reduce pain
Cervical spine (C5-C6, C6-C7)
- Neck pain radiating to the shoulder, arm, fingers
- Numbness and tingling in the fingers (often ring finger and little finger)
- Dizziness, tinnitus, visual disturbances
- Occipital headaches
- Arm weakness, impaired fine motor skills
- Limited head rotation and tilting
- With large hernias — impaired coordination, gait
Thoracic spine (Th6-Th12)
- Chest pain, often mimicking angina
- Girdling pain along intercostal nerves
- Numbness in the abdomen or chest area
- Worsening with deep breathing and twisting
- Occurs less frequently, but often with severe neurological symptoms
When to seek urgent care
- Impaired pelvic organ function (urination, defecation)
- Progressive weakness in extremities
- Cauda equina syndrome — emergency condition
- Intractable pain not relieved by analgesics
- Numbness in the perineal area
Diagnosis of Herniated Disc
Accurate diagnosis is the foundation of successful treatment. The comprehensive approach combines clinical examination with modern imaging methods.
Diagnostic Methods:
- MRI (magnetic resonance imaging) — the "gold standard" for diagnosing disc herniations. It visualizes soft tissues: disc, nerve roots, spinal cord, ligaments. MRI shows herniation size (accurate to tenths of a millimeter), degree of nerve compression, and condition of adjacent discs
- CT (computed tomography) — complements MRI, especially for assessing bone structures and calcifications
- X-ray — assessment of spinal alignment, disc height, detection of osteophytes and instability
- Electroneuromyography (ENMG) — when necessary, to assess nerve conduction and degree of damage
How regenerative treatment Uses Diagnostics:
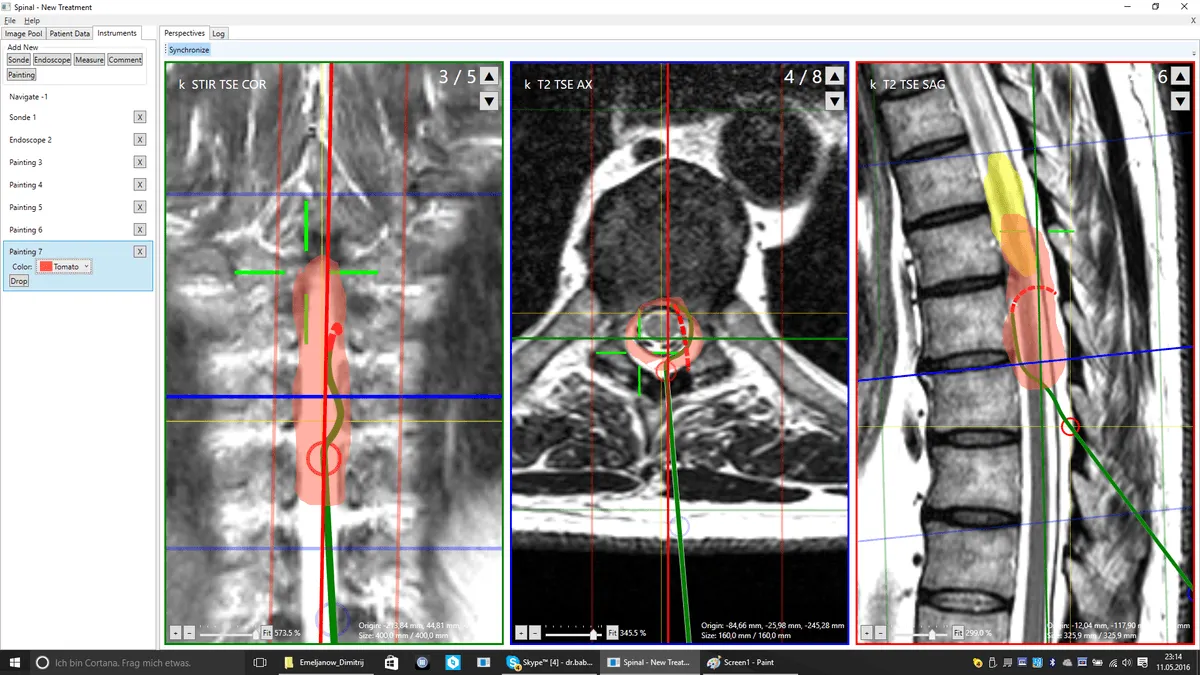
MRI/CT images are uploaded to the navigation system, which creates a 3D model of the patient's spine. On this model, the surgeon plans precise coordinates for micro-invasive access to each damaged disc: insertion angle (accurate to 1°), penetration depth (to 1 mm), and optimal trajectory excluding damage to neural structures.
Free MRI Evaluation
- Send MRI images online
- A clinic specialist will personally assess your case
- You will receive a report within 1–3 business days
- No obligations and free of charge
Herniated disc: treatment options and what is known about them
The treatment plan is made by the clinic doctor after an examination and a review of your images. The table shows the options usually discussed for this diagnosis and how well they have been studied.
| Option | What to expect | How well studied |
|---|---|---|
| Exercise therapy and physiotherapy | Reduces pain, strengthens muscles, improves function; the basis of treatment | Well studied, recommended |
| Painkillers and NSAIDs | Ease pain during flare-ups; long-term use is limited by side effects | Moderate evidence |
| Epidural or perineural injection | Reduces radicular pain for weeks or months, helps get through a flare-up | Moderate evidence |
| PRP / CGF | Concentrate from your own blood; may reduce pain, growth of new tissue has not been shown | Little data |
| BMAC / MFAT | Cell preparations from bone marrow or fat; more expensive, no proven advantage over PRP | Little data |
| Microdiscectomy | If conservative treatment does not help or there is an indication | When indicated — the doctor decides |
We send your request to several partner clinics. Some will suggest conservative treatment or injections, others surgery; each clinic quotes its own conditions and price. We help you compare the options.
Regenerative methods: realistic expectations
In most patients with a herniation or protrusion, leg or arm pain eases markedly within 6–12 weeks without surgery. Staying active, exercise therapy and painkillers help; for severe radicular pain, an epidural or perineural injection may be used. Intradiscal injections of PRP and cells are still experimental: the studies are small and disc regeneration has not been shown.
When surgery is discussed. Urgently — for leg weakness, numbness in the saddle area or bladder problems. Electively — if severe radicular pain does not ease within 6–12 weeks of treatment.
If an injection helps, the effect usually builds up over 6–12 weeks, and the result is assessed after 2–3 months. No clinic can guarantee a result.
Scientific evidence
Studies of regenerative methods show mixed results. Clinic physicians rely on research including the following:
- Tuakli-Wosornu YA et al. Lumbar Intradiskal Platelet-Rich Plasma (PRP) Injections: A Prospective, Double-Blind, Randomized Controlled Study. PM R, 2016.
- Lurie JD et al. Surgical versus nonoperative treatment for lumbar disc herniation: eight-year results for the Spine Patient Outcomes Research Trial. Spine, 2014.
Next steps: Treatment methods · Treatment cost · How treatment in Germany is organised · Contact a coordinator
Frequently Asked Questions about Herniated Disc Treatment


Clinic and method matching — free of charge
Describe your case and attach your MRI report. We will identify clinics that use the relevant methods and forward your request to them. No obligation; we reply within 24 hours.
Send a request