
 Русский
 English
 Deutsch
 Español
 العربية
 中文
 Türkçe
 Français
 Italiano
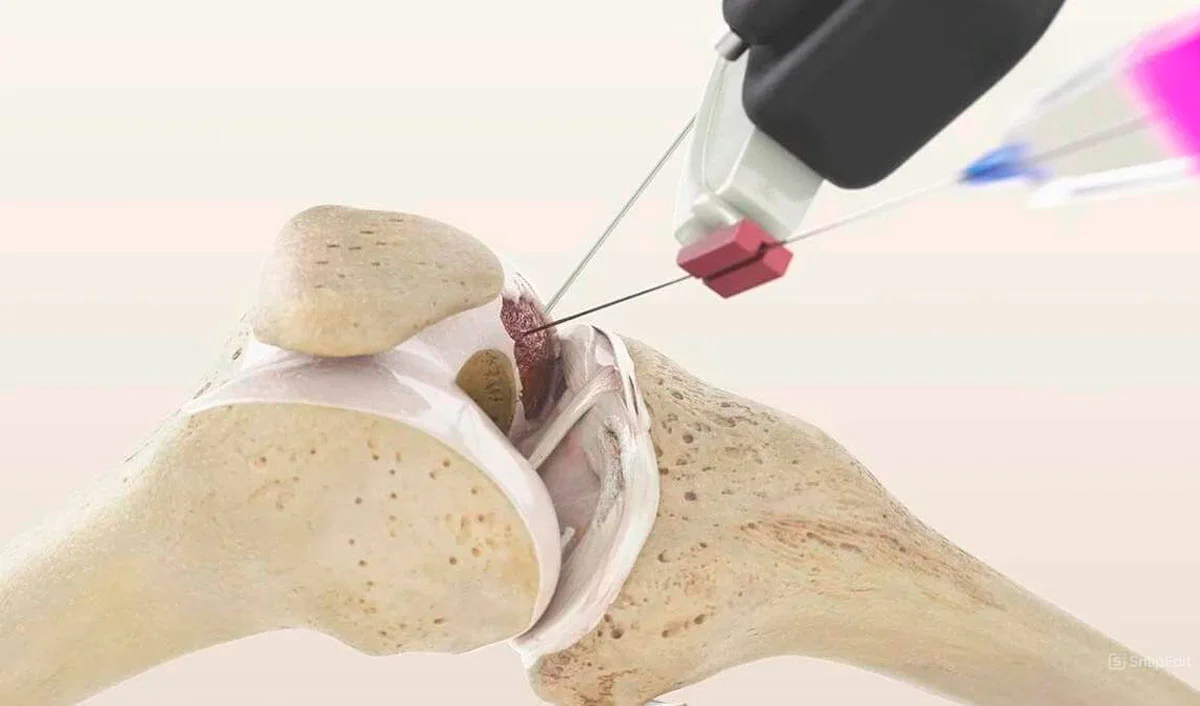
What is knee osteoarthritis (gonarthrosis)?
Knee osteoarthritis (gonarthrosis) is a degenerative-dystrophic disease in which the cartilage tissue of the knee joint is destroyed, leading to pain, limited mobility, and deformity. Read more about the stages of the disease in our article on the 4 stages of gonarthrosis.
This is the most common osteoarthritis disease. According to WHO data, about 10% of men and 13% of women over 60 suffer from gonarthrosis. In Germany, more than 190,000 knee joint replacement surgeries are performed annually — this is one of the most common orthopedic procedures.
Stages of gonarthrosis (Kellgren-Lawrence):
- Grade I — doubtful radiographic signs, minimal osteophytes
- Grade II — moderate joint space narrowing, definite osteophytes
- Grade III — significant joint space narrowing, subchondral sclerosis, multiple osteophytes
- Grade IV — marked joint space narrowing, large osteophytes, deformation of bone contours
Types of involvement:
- Medial — involvement of the medial compartment (most common)
- Lateral — involvement of the lateral compartment
- Patellofemoral — involvement of the patella
- Total — involvement of all compartments
Facts about knee osteoarthritis (gonarthrosis)
- ICD-10: M17
- Prevalence: 10-13% of population over 60 years
- Gender: women affected 1.5-2 times more often
- Joint replacement: 190,000+ surgeries/year in Germany
- Obesity: increases risk 4-5 times
Symptoms of knee osteoarthritis (gonarthrosis)
Early signs
- Pain when climbing stairs
- Morning stiffness (up to 30 minutes)
- Crunching (crepitus) in the knee
- Discomfort after prolonged sitting
- Intermittent joint swelling
Progression
- Constant pain while walking
- Limited flexion/extension
- Joint instability
- Varus or valgus deformity
- Synovitis (joint effusion)
Late Stages
- Pain at rest and at night
- Marked leg deformity (O- or X-shaped)
- Inability to fully extend
- Quadriceps muscle atrophy
- Need for cane or crutches
Knee Prosthesis vs regenerative treatment
| Criterion | Total Joint Replacement | Arthroscopy | Regenerative treatment |
|---|---|---|---|
| Principle | Joint replacement with metal | Irrigation, fragment removal | Cartilage regeneration with own cells |
| Anesthesia | General / spinal | General / spinal | No general anesthesia (local anesthesia) |
| Hospitalization | 7-14 days | 1-2 days | None — home same day |
| Rehabilitation | 3-6 months | 2-6 weeks | Several days |
| Cartilage Regeneration | ❌ Joint removed | ❌ Does not restore cartilage | ✅ Restoration of cartilage covering |
| Both Knees at Once | ❌ One only | Possible, but risky | ✅ Yes — both knees + other joints |
| Active Sports After | Limited | Possible | ✅ Full activity |
How regenerative treatment treats knee osteoarthritis
3D Planning
Knee joint MRI is loaded into Navigation system. Zones of maximum cartilage damage, menisci condition, ligaments, subchondral bone are identified. A plan for minimally invasive access is developed.
Biomaterial Preparation
CGF with high concentration of growth factors and cytokines is obtained from blood. MFAT with mesenchymal stem cells capable of differentiating into chondrocytes is obtained from adipose tissue.
Precise Injection
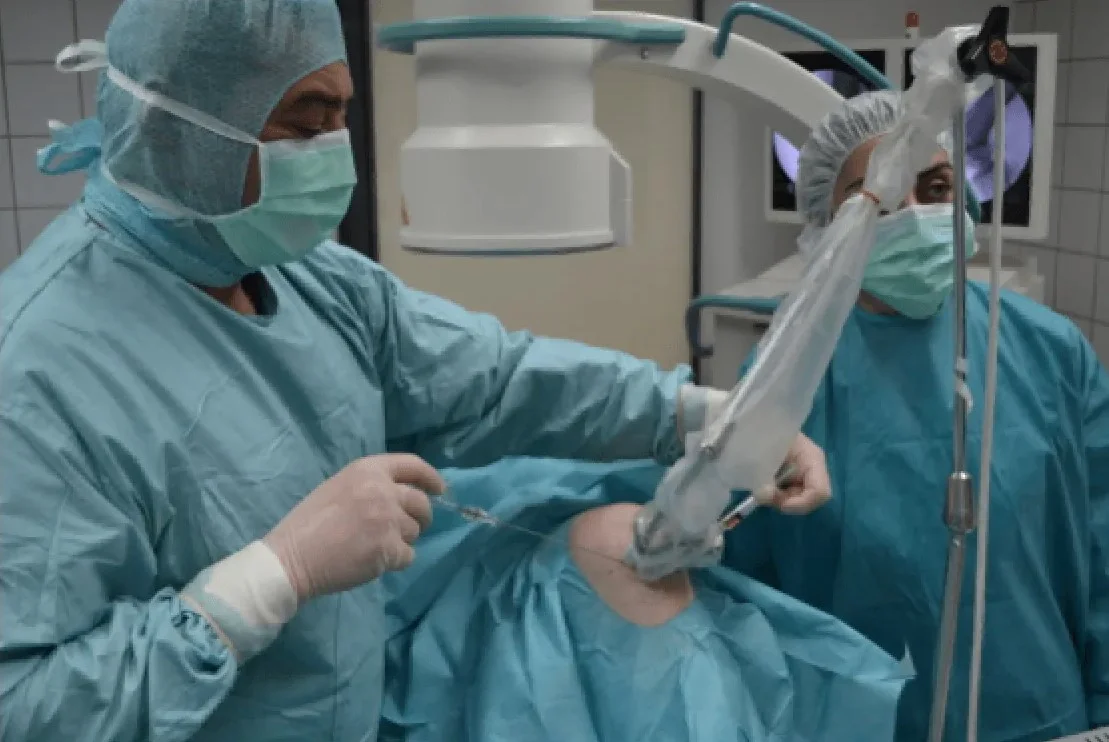
Under Ultrasound guidance guidance, concentrates are injected directly into damage zones — medial/lateral compartment, patellofemoral region, menisci area, subchondral cysts.
Regeneration
Stem cells differentiate into chondrocytes, synthesis of new cartilage matrix begins. Growth factors reduce inflammation, improve blood supply. After 3-6 months — cartilage restoration visible on follow-up MRI.
Why regenerative treatment is effective for knee osteoarthritis
Knee osteoarthritis was considered irreversible: cartilage is destroyed and cannot be restored. Traditional medicine offers painkillers, "lubricants" (hyaluronic acid), and ultimately — joint replacement. Regenerative treatment changes this paradigm — true cartilage regeneration of the knee joint is possible for the first time.
Mechanism of Action in Knee Osteoarthritis:
- Chondrogenesis — MFAT stem cells differentiate into chondrocytes and synthesize hyaline cartilage (type II collagen, proteoglycans)
- Anti-inflammatory Effect — suppression of chronic inflammation accelerating destruction (reduction of IL-1β, TNF-α, MMP-13)
- Meniscus Regeneration — simultaneous restoration of damaged menisci, recovery of shock absorption
- Synovial Fluid Normalization — improved lubrication and cartilage nutrition
Key Difference: Regenerative treatment is not a "lubricant" or pain reliever. It is biological regeneration, confirmed by follow-up MRI: increased cartilage thickness, reduced subchondral edema, restoration of joint space.
Regenerative treatment for Knee Osteoarthritis
- Both knees at once — + hip joints + spine
- Ultrasound guidance — precise navigation
- Without anesthesia — local anesthesia
- Sports without restrictions — after recovery
- Does not interfere with joint replacement — if needed later
Regenerative method Advantages
A broad range of indications
Regenerative methods are used for many orthopaedic and spinal conditions. Some cases still call for surgery.
No anesthesia or incisions
Outpatient treatment via 0.3-1.5 mm puncture. No general anesthesia or hospitalization.
No age restrictions
Regeneration at any age. Safe for chronic conditions and anesthesia intolerance.
Rapid improvement
Concentrates have analgesic and anti-inflammatory properties. Relief within days.
Multiple zones at once
Simultaneous treatment of multiple discs or joints in one procedure.
Home the same day
No crutches, braces or rehabilitation needed. MRI follow-up at 8-16 weeks.
Regenerative treatment Technology

Navigation system
Intraoperative robotic navigation system. Provides precise access to deep structures with 1 mm and 1 degree accuracy.
Ultrasound guidance
Device for intervention under sonographic control. Eliminates open surgeries with real-time visual monitoring.
Frequently Asked Questions About Knee Osteoarthritis Treatment

Clinic and method matching — free of charge
Describe your case and attach your MRI report. We will identify clinics that use the relevant methods and forward your request to them. No obligation; we reply within two working days.
Send a request